
Typical requirements
| Motors in one surgical robot | Several dozen, to transmit the surgeon's movements (maxon) |
|---|---|
| Autoclave cycle for sterilisable motors | 134 °C ±4 °C, 100% RH, 2.3 bar, 18 min (maxon) |
| Autoclave life (published) | More than 1,000 cycles with sensors; up to 2,000 without |
| Micro motor speed (published range) | Up to 120,000 rpm at 4–22 mm diameter (maxon ECX SPEED) |
| Hip moment in walking (research data) | About 1.3 Nm/kg, 97 Nm peak for a 75 kg adult at 1.6 m/s |
| Quasi-direct-drive hip actuator (research example) | 17.5 Nm nominal, 42 Nm peak, 8:1 ratio, 0.77 kg |
| IEC 80601-2-77 status | EN IEC 80601-2-77:2021 + A1:2023, consolidated from February 2024 |
Machinery we specify motion for
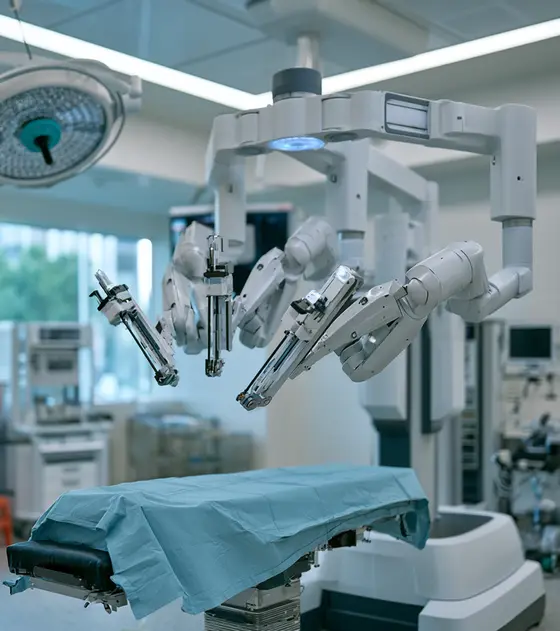
- Robotic-assisted surgical systems
- Robotic instrument and endoscope drives
- Surgeon consoles and haptic controllers
- Surgical microscopes
- Surgical tables
- Rehabilitation exoskeletons
- Powered prosthetics
- Rehabilitation and therapy devices
What surgical and medical robots demand from motion
This page goes deeper on robots than our medical and laboratory overview, which covers IEC 60601-1 component evidence, the basic frameless-motor and strain-wave joint, and lab automation. Here the focus is the rest of the robot, and the robots that work on or with the patient’s body.
A medical robot is rarely one big axis. It is many small ones, each with a different job:
- Arm joints position the instrument and must hold pose safely.
- Instrument drives move a wrist and jaws a few millimetres across, often through cables, behind a sterile barrier.
- Consoles and hand controllers read the surgeon’s hand and push back with haptic force.
- Wearable joints in exoskeletons and prosthetics move with a person, so they must be light, quiet and safe to push against.
maxon, whose motors are used in surgical systems, says several dozen motors are needed in one surgical robot to transmit the surgeon’s movements, and stresses zero cogging and haptic feedback. Harmonic Drive’s medical page lists surgical robots, surgical microscopes and exoskeletons as uses for zero-backlash, quiet gearing.
Where each component sits
| Subsystem | Motion | Typical components | Key requirement |
|---|---|---|---|
| Patient-side arm | Several rotary joints | Frameless motor, strain-wave gear, dual encoders, brake, embedded drive | Short joints, safe hold, low heat |
| Instrument drive unit | Several small rotary axes pulling cables | Micro brushless or coreless motors, gearheads, encoders | Compact, precise, behind sterile barrier |
| Surgeon console | Hand controller axes | Low-cogging direct drive or coreless motors, high-resolution encoders | Smooth haptic feel |
| Surgical microscope | Focus, zoom, tilt, balance | Micro motors, steppers, compact strain-wave gears | Optical stability, no vibration |
| Surgical table | Height, tilt, sections | Electric linear actuators | Holds load on power loss |
| Exoskeleton | Hip, knee, ankle | Strain-wave or low-ratio gears, brushless motors, absolute encoders | Torque per kg, backdrivability |
| Powered prosthetic | Knee, ankle, hand | Brushless motors with gears or screws | Mass, battery life, noise |
Sterile barrier and sterilisation: decide first
The most important early decision is which parts must be sterilised. It changes the motor technology, the materials and the cost.
- Behind the sterile barrier. In many systems the arm is draped and the instrument attaches to its drive unit through a sterile adapter, so the motors stay outside the sterile field and need only to be cleanable. This is usually the cheaper route.
- In the sterile field. Handheld powered tools and some instruments carry their own motor. maxon publishes its sterilisable brushless motors for an autoclave cycle of 134 °C ±4 °C, 100% relative humidity, 2.3 bar and 18 minutes, with more than 1,000 cycles for drives with sensors and up to 2,000 without. Brushed motors are not autoclavable. maxon also states that ethylene oxide sterilisation is unrestricted for all its catalogue products.
Small motors for instruments run fast and drive through high-ratio gearheads. maxon’s ECX SPEED platform, for example, runs at up to 120,000 rpm at 4–22 mm diameter. Coreless and slotless designs have no cogging, which helps both haptics and slow motion.
Exoskeletons and prosthetics: torque, mass and backdrivability
Wearable robots turn the usual sizing upside down. The load is the person, the actuator rides on the person, and the joint must never fight them.
Published gait data gives the scale. In the hip exoskeleton study by Yu et al., the peak hip moment in walking is about 1.3 Nm/kg, or 97 Nm for a 75 kg adult at 1.6 m/s, with peak joint speed around 2.3 rad/s. Their exoskeleton targets partial assistance of 19.4 Nm, not the full moment, and its quasi-direct-drive actuator gives 17.5 Nm nominal and 42 Nm peak through an 8:1 gear at 0.77 kg. They measured backdrive torque of about 0.4 Nm and an actuator bandwidth of 62.4 Hz.
Worked example: strain-wave or low-ratio gear for a hip joint
Assume a 20 Nm continuous, 40 Nm peak assistance target at up to 3 rad/s (about 29 rpm), and a motor whose rotor inertia is 50 kg·mm². These are illustrative figures, not a design.
- At 100:1 strain-wave. The motor needs about 0.2 Nm continuous and 0.4 Nm peak plus gear losses, at about 2,900 rpm. Reflected inertia at the joint is 50 × 100² = 500,000 kg·mm², or 0.5 kg·m². That is heavy for a leg to swing, and friction through a strain-wave gear adds to the backdrive torque.
- At 8:1. The motor needs 2.5 Nm continuous and 5 Nm peak, at about 230 rpm, so it is larger and heavier. Reflected inertia is only 50 × 8² = 3,200 kg·mm², or 0.0032 kg·m², about 150 times less.
- Decision. If the joint must be transparent to the user, as in assistive gait, the low-ratio route wins despite the bigger motor. If it must deliver high torque in a compact package and lead the patient’s movement, as in some rehabilitation devices, a strain-wave gear or a complete harmonic actuator is usually the better fit.
- Check. Run both options through the real gait torque and speed cycle, and compare RMS motor heat, battery energy and mass at the joint.
Powered prosthetics face the same trade-off with tighter mass and battery limits. Size knee and ankle drives from published gait moments for the user’s mass and activity, and include the noise target, which users notice quickly.
Consoles, haptics and microscopes
Hand controllers read the surgeon’s hand and feed force back, so they need very low friction and cogging, and high-resolution encoders. Coreless motors, ironless direct drives such as the Akribis ACD and thin capacitive encoders suit these axes. Netzer lists tolerance to EMI, RFI and magnetic fields among its encoder features, which helps in a joint packed with motors and brakes.
Surgical microscopes move heavy optics that must not shake. Harmonic Drive cites backlash-free, smooth movement for optical stability in focusing and positioning. Use low-backlash gearing, brakes or balancing on the stand axes, and quiet micro motors or steppers for focus and zoom.
Surgical tables and patient positioning
Operating tables have their own particular standard, IEC 60601-2-46, which applies alongside IEC 80601-2-77 when a table forms part of a robotic system, according to the EVS listing of that standard. For motion, tables are slow, high-force, low-duty axes. Choose self-locking screw actuators such as the GT44, define what each axis does on power loss, and coordinate table moves with the robot so the patient and the instrument stay registered.
Typical pitfalls
- Deciding sterilisation late. Moving a motor into the sterile field after the design freeze means a different motor.
- Choosing ratio on torque alone. High ratios cost backdrivability and add reflected inertia, which matters for haptics and wearables.
- Specifying encoder resolution, not accuracy. Tool-tip error comes from accuracy across every joint.
- Forgetting the drive’s thermal path. A drive sealed in a joint may have no airflow at all.
- Ignoring audible noise. PWM whine and gear noise are noticed in theatre and in daily prosthetic use.
What to send us
For each axis send the motion, range, torque or force, speed and duty, the envelope and mass budget, bus voltage, feedback interface and brake needs. Say whether the part sits in the sterile field and how it is sterilised, which safety standard the device follows, and the evidence your risk file needs. Our specialist engineering and supply partners will propose matched motor, gear, encoder and drive sets.
Frameless motors for surgical robots
Frameless rotor and stator kits build straight into a surgical arm joint, sharing its bearings and housing, so the joint is as short as possible and keeps a hollow centre for cables. Low-voltage windings on a 48 V class bus suit the low-voltage drives that medical arms prefer. Specify continuous torque at the joint's real thermal limit, which is usually set by gear lubricant or encoder temperature rather than the winding, plus peak torque, speed, OD, ID and stack length. Ask for cogging torque and its frequency, which datasheets rarely show, and for insulation and creepage data for the device's safety file.
- Surgical arm joints: shoulder, elbow and wrist axes
- Endoscope holders: compact joints with hollow cable path
- Patient-side carts: column and set-up joints
- Haptic consoles: smooth, low-cogging direct drive
Available through our supply network
All frameless and torque motors →Specify frameless and torque motors for surgical and medical robotics →
Strain-wave gears and harmonic actuators for exoskeletons
Strain-wave gears give zero backlash and a high ratio in one flat stage, which suits surgical arm joints, microscope stands and the knee and hip joints of rehabilitation exoskeletons. Ultra-flat and hollow-shaft sets keep joints thin and leave room for cables. The trade-off is backdrivability: a 100:1 gear multiplies the motor's reflected inertia by 10,000 and makes the joint stiff to push by hand. Complete harmonic actuators combine gear, motor, encoders, brake and sometimes the drive, which shortens development. Specify rated and peak torque, ratio, bore, axial length, mass and whether the joint must be backdrivable.
- Rehabilitation exoskeletons: hip and knee joints
- Surgical arms: wrist and elbow reducers
- Surgical microscopes: balanced arm and tilt axes
- Therapy robots: upper-limb joints
Available through our supply network
All gearboxes and harmonic drives →Specify gearboxes and harmonic drives for surgical and medical robotics →
Micro motors for surgical instruments and microscopes
Small brushless, slotless and coreless motors drive instrument wrists and jaws, endoscope articulation, microscope focus and zoom, and powered handheld tools. Slotless and coreless designs have no cogging, which helps haptic feel and slow, smooth motion. Decide early which motors sit in the sterile field: those must be brushless and rated for autoclave cycles, because brushed motors are not autoclavable. Those behind the sterile barrier, in the instrument drive unit, can be conventional. Specify speed, torque at the gearhead output, diameter, sterilisation method and cycle count, noise and any encoder.
- Instrument drive units: cable-driven wrist and jaw axes
- Endoscope holders: articulation and insertion
- Surgical microscopes: focus, zoom and illumination
- Prosthetic hands: finger and wrist drives
Available through our supply network
All servo and stepper motors →Specify servo and stepper motors for surgical and medical robotics →
Encoders for surgical robots
Each joint usually needs fast motor-side feedback and a high-accuracy absolute encoder on the output, so the controller knows true joint angle after the gear at power-up and can detect gear wind-up. Thin hollow-shaft capacitive and inductive encoders fit around the joint's cable bore and tolerate magnetic fields from the motor and brake. Specify accuracy, resolution, bore, axial height, interface such as BiSS-C or SSI, update rate and temperature. For safety functions ask what diagnostic data the encoder can supply.
- Surgical arm joints: output-side absolute angle
- Instrument drives: motor-side commutation and position
- Exoskeletons: joint angle for gait control
- Haptic consoles: high-resolution hand-controller feedback
Available through our supply network
All encoders and feedback →Specify encoders and feedback for surgical and medical robotics →
Servo drives for medical robots
Board-level servo drives sit inside the joint or the instrument drive, which shortens motor leads and turns the arm harness into a power bus plus EtherCAT or CANopen. Low-impedance medical joint motors need drives with a high PWM and current-loop frequency to keep current ripple and audible noise down. Specify bus voltage, continuous and peak current, feedback types including dual BiSS-C, the fieldbus, and the safety functions such as STO with a stated SIL. Ask for thermal data in a sealed housing, because a joint drive may have no airflow.
- Surgical arm joints: embedded EtherCAT drives
- Instrument drive units: multi-axis micro drives
- Exoskeletons: battery-powered joint drives
- Haptic consoles: low-noise current control
Available through our supply network
All servo drives →Specify servo drives for surgical and medical robotics →
Actuators for surgical tables and patient positioning
Surgical and treatment tables, patient positioners and rehabilitation frames use electric linear actuators for height, tilt and section adjustment. These are low-duty, high-force axes where quiet running, self-locking under load and a safe response to power loss matter more than speed. Specify force in push and pull, stroke, speed, duty cycle, supply voltage, IP rating for cleaning, and whether the actuator must hold a patient load if power fails. Small linear steppers suit short, precise moves in instruments and therapy devices.
- Surgical tables: height, tilt and back section
- Patient positioners: lift and slide
- Rehabilitation frames and gait trainers: body-weight support
- Therapy devices: short-stroke linear stages
Available through our supply network
All linear actuators →Specify linear actuators for surgical and medical robotics →
Slip rings for rotating instrument and arm interfaces
Most surgical joints have limited rotation and route cables through a hollow centre. A slip ring is needed only where an axis turns continuously and still carries power or signals, such as an instrument roll axis, a rotating endoscope or camera head, or a rotating table on a lab or rehabilitation robot. Specify circuits, currents, signal types and any Ethernet, the bore and OD, speed and the electrical noise the signals can tolerate. Gold-on-gold capsule rings keep electrical noise and torque low in small envelopes.
- Instrument roll axes: power and sensor signals
- Rotating camera and endoscope heads: video and control
- Rehabilitation robots: continuous-rotation joints
Available through our supply network
All slip rings →Specify slip rings for surgical and medical robotics →
Standards to have in view
- IEC 80601-2-77 (robotically assisted surgical equipment, RASE and RASS)
- IEC 60601-1 (medical electrical equipment, basic safety and essential performance)
- IEC 60601-1-2 (EMC for medical electrical equipment)
- IEC 60601-2-46 (operating tables)
- ISO 14971 (medical device risk management)
- ISO 13485 (medical device quality management)
- ISO 13482 (personal care robots, for non-medical wearable robots)
Which standards apply depends on the end product and its market. Your engineer will confirm what the component itself needs to meet.